What Is The Best Treatment For Jawline Definition?
- Facial Ageing General
- October 14, 2026


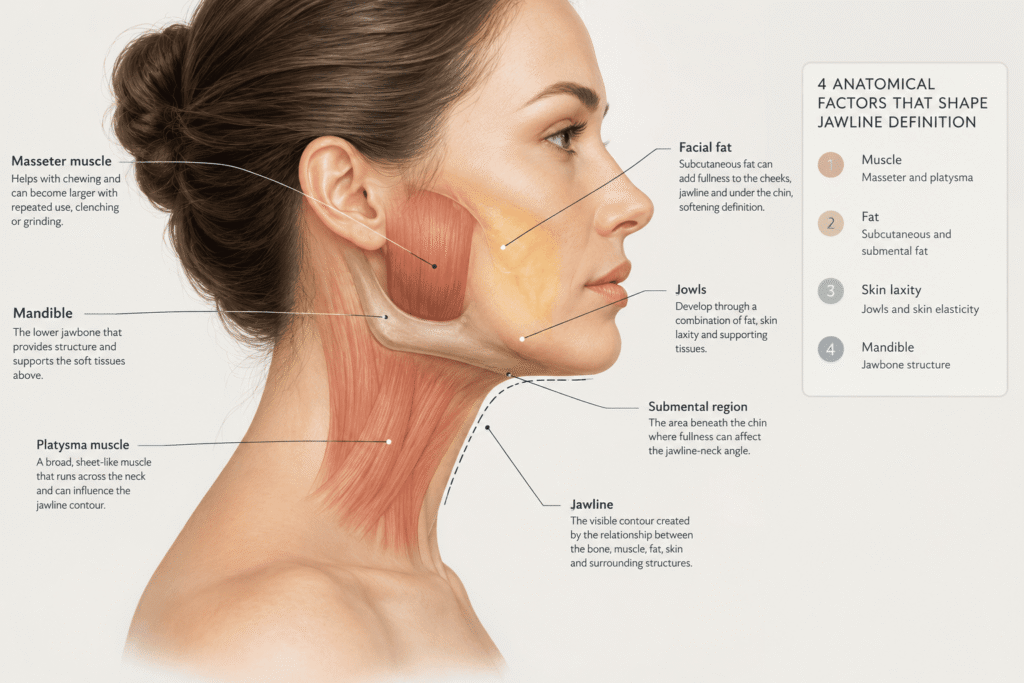
The best approach to jawline definition depends on the underlying cause. Four key anatomical factors influence the appearance of the jawline: muscle size and downward pull, facial fat distribution, skin laxity and the structure of the mandible (jawbone). The chin and surrounding facial features also affect the overall contour. A personalised assessment helps identify which factors are contributing to the concern and whether surgical and non-surgical treatment options may be appropriate. There is no single approach that suits everyone.
A well-defined jawline is something many people would like to achieve. During consultations, I often hear patients describe their concern as their cheek blending into their neck, or feeling that their jawline has lost the distinct angle and contour it once had.
But what actually determines jawline definition?
The answer is more complex than you might think.
After nearly 13 years working in aesthetic medicine, one of the most important things I have learnt is that two people can have very similar concerns about their jawline for completely different anatomical reasons.
For one person, muscle bulk of the masseter muscle may contribute to a wider lower face. For another, the appearance of the jawline may be influenced by subcutaneous fat, skin laxity, jowling or the underlying structure of the mandible. Often, several factors contribute at the same time.
There is no single best treatment for jawline definition. The most appropriate approach depends on understanding what is causing the concern in the first place.
In this article, I’ll explain the four main anatomical factors I assess when someone presents with concerns about their jawline, why the chin and surrounding facial structures also matter, and what you should understand before considering treatment.
What determines jawline definition?
Jawline definition is influenced by the relationship between the underlying bone, the muscles, the fat compartments and the skin and soft tissues covering them.
I assess four key anatomical factors:
- Muscle — particularly the masseter and platysma.
- Fat — including subcutaneous and submental fat.
- Skin laxity — and the development of jowls.
- The mandible — the bone that forms the lower jaw.
The chin, mid-face and overall facial proportions must also be considered because the jawline does not exist in isolation.
Let’s look at each factor in more detail.
1. Muscle: Can your jaw muscles change the shape of your face?
Two muscles are particularly relevant when assessing jawline definition: the masseter and the platysma.
The masseter muscle
The masseter is one of the main muscles responsible for chewing. It sits at the side of the jaw and helps elevate the mandible when you bite down.
Like other muscles, the masseter can increase in size through repeated use. This is known as muscle hypertrophy.
In some people, the masseter becomes more prominent in association with teeth clenching or bruxism (teeth grinding). In others, a naturally strong masseter contributes to their facial shape.
When the muscle becomes larger, it can create a wider, squarer appearance at the angle of the jaw.
Interestingly, this change can happen gradually over several years. Some patients only recognise it when comparing recent photographs with older ones, commenting that their face never used to look this shape.
During an assessment, I ask patients to bite down while I palpate the masseter muscles. This helps me evaluate their size, prominence and muscular contraction in the context of their overall facial anatomy.
It is important to understand that a wider lower face does not automatically mean that the masseter is enlarged. The underlying bone structure and surrounding soft tissue also influence facial width.
If you suspect that you grind or clench your teeth, it is worth discussing this with your dentist, particularly if you experience tooth wear, jaw discomfort or morning jaw fatigue.
To understand how the masseter muscle size influences facial width, read out article about masseter muscles and facial slimming.
The platysma muscle
The platysma is a broad, thin sheet-like muscle that extends across the neck and attaches into the lower face and jawline region.
Its function includes helping to depress the mandible and contributing to tension in the skin of the neck.
When the platysma contracts, its downward pull can influence the appearance of the lower face and neck. This is particularly noticeable in some people when they animate their facial muscles.
During a consultation, I ask patients to say “eeee” to help demonstrate platysma activity. I can then assess how the muscle contracts and how its movement relates to the surrounding tissues.
This is one reason I don’t assess jawline concerns solely by looking at a photograph or examining the face at rest. Muscle activity can provide additional information about what is contributing to the appearance of the jawline.
Learn more about platysma anatomy on our neck consultation page.
2. Subcutaneous fat: Is facial fullness hiding your jawline?
One of the most common misconceptions I encounter is that a person who cannot see a distinct jawline must have poor bone structure.
That isn’t necessarily the case.
The underlying jawbone may be well defined, but the soft tissue covering it can soften the visible contour.
Subcutaneous fat is the fat located beneath the skin. Its distribution varies naturally between individuals and can contribute to fullness across the cheeks, lower face and jawline.
There are several distinct concerns worth differentiating.
Submental fullness
The submental region is the area directly beneath the chin. Fullness here can soften the transition between the chin and neck, making the jawline less distinct.
Some people describe this as having a “double chin”.
However, the appearance of this area can also change with head position. Looking down naturally causes the chin and neck tissues to compress and fold. This alone does not establish that someone has excess fat or requires treatment.
Fullness along the jawline
Some people have naturally fuller tissue over the lower face, which can soften the angle between the jaw and neck.
The important question is whether the fullness is related to fat distribution, underlying bone structure, skin laxity or a combination of these factors.
These causes can look similar from the front but require different considerations when assessing the face.
Why natural fullness matters
I once assessed a patient who wanted a more defined jawline because she felt her face looked too full.
On examination, the fullness was a natural feature of her facial anatomy rather than an isolated problem that I felt needed correcting.
I explained that natural facial fullness contributes to the appearance of youthful skin and provides underlying soft-tissue support. As we age, facial fat distribution and volume change, and some areas can lose fullness over time.
In this case, I did not recommend treatment.
I think this is an important point, particularly for younger patients who compare their faces with highly sculpted images online. Natural fullness is not automatically something that needs to be removed or reduced.
My role is not to convince someone that every feature they dislike needs correcting. It is to assess their anatomy, explain what I see and help them make an informed decision.
3. Skin laxity: When the jawline begins to soften
Skin and soft-tissue changes can also influence jawline definition.
As we age, changes in skin elasticity, connective tissue, fat distribution and the supporting structures of the face can contribute to a softer lower-face contour.
One common concern is the development of jowls.
What causes jowls?
Jowls are the areas of tissue that become more prominent along the lower sides of the face, around the jawline and towards the chin.
Their development is multifactorial. Changes in skin elasticity, facial fat compartments and the supporting retaining ligaments all contribute to the changing contour of the lower face.
Jowls are different from fullness directly beneath the chin. Although both can make the jawline appear less defined, they are anatomically distinct concerns.
Skin laxity can also coexist with subcutaneous fullness. This is why simply identifying an area that looks fuller does not tell us what is causing it.
Why skin laxity and fullness must be distinguished
During an assessment, I examine the skin and underlying tissues, including their mobility and elasticity. I also consider how the lower face looks from different angles and how the skin sits over the underlying structures.
A concern primarily related to skin laxity is different from one primarily related to fullness beneath the skin.
Addressing one factor does not necessarily address the other.
For example, an approach intended to reduce fullness would not automatically correct skin laxity. Equally, an approach directed at skin laxity would not necessarily change the amount or distribution of underlying fat.
Some patients have a combination of concerns, which is why a personalised assessment may involve discussing different treatment modalities rather than assuming one approach will address everything.
4. The mandible: Your underlying jawbone structure
The mandible is the bone that forms your lower jaw. It provides structural support for the soft tissues above it and plays a major role in determining the shape and proportions of the lower face.
I often think of the mandible as the support beams of a house. The structures above it depend, in part, on the foundation beneath them.
The shape, width, angle and projection of the mandible vary considerably between individuals. These differences are a normal part of human anatomy.
Someone with a naturally prominent jaw angle may have a more defined contour than someone with a narrower or less prominent underlying structure, even if their soft tissues are otherwise similar.
Why the chin matters when assessing the jawline
The chin is particularly important when evaluating the jawline from the side.
I have seen patients present with the concern that they have no jawline definition in profile. On assessment, one patient had a receded or regressed chin, which contributed to the appearance that the jawline was effectively “cut off” at the front.
The concern was described as a jawline problem, but the chin was an important part of the explanation.
This is why I assess the relationship between the chin, mandible, lower face and neck rather than focusing on one isolated area.
Mid-face changes and skin laxity can also influence the overall facial proportions, so these may need to be considered as part of the broader assessment.
Not every concern related to bone structure can be addressed in the same way as a concern related to the soft tissues. During a consultation, I explain what the individual’s anatomy allows us to consider and establish realistic expectations about what may be achievable.
How I assess jawline definition during a consultation
When someone comes to see me about their jawline, I don’t start by deciding which treatment they need.
I start by assessing their anatomy.
My assessment includes examining the face from the front, at a 45-degree angle and in side profile. Each view provides different information about facial proportions, the jaw angle, chin projection and the transition between the face and neck.
I also assess several anatomical features:
- Muscle activity: I palpate the masseters during clenching and observe platysma contraction.
- Underlying bone: I assess the shape and prominence of the mandible and the position of the chin.
- Soft-tissue fullness: I examine the distribution of subcutaneous fat and any fullness beneath the chin.
- Skin and tissue support: I assess skin elasticity, tissue mobility and the presence of jowling.
- Overall facial harmony: I consider how the jawline relates to the chin, cheeks, mid-face and upper face.
This process helps distinguish between concerns that may appear similar but have different underlying causes.
It also helps establish whether the desired outcome is realistic and whether any intervention is appropriate.
So, what is the best treatment for jawline definition?
The most appropriate approach depends on the anatomical factors contributing to the concern.
There is no universal treatment that suits everyone, and a treatment that may be appropriate for one person may not be suitable for another.
Broadly, management may involve discussing surgical or non-surgical treatment modalities, depending on the assessment, the individual’s goals and their suitability for the available options.
These decisions should be made during a personalised consultation with an appropriately qualified practitioner who can assess the relevant anatomy, explain the available options and discuss their limitations and risks.
It is equally important to recognise when treatment is unlikely to provide the result someone is seeking, or when no treatment is the most appropriate recommendation.
The goal should not be to force every face into the same jawline shape. It should be to understand the individual’s anatomy and determine what, if anything, is appropriate for them.
Why I don’t recommend chasing an exaggerated jawline
Social media has made highly angular jawlines increasingly visible. Before-and-after photographs can create the impression that everyone should have a sharp, straight line from the chin to the angle of the jaw.
But these images do not always tell the whole story.
Photographs can be influenced by lighting, head position, camera angles, editing and image selection. Images taken shortly after a procedure may also show temporary swelling, which should not be mistaken for a long-term result.
Anatomy matters, too.
Female faces often have softer jawline contours than male faces, although there is considerable natural variation within both groups. A very angular jawline may look harmonious on one person but disproportionate on another.
Imagine someone with a naturally soft, narrow upper and mid-face who wants a substantially wider, square lower face. If the desired change is out of proportion with their existing features, the result may not look as harmonious as they expected.
I have seen how patients can become focused on a particular feature or image without considering how it relates to their face as a whole.
This is why I believe facial assessment should consider the overall balance of the face rather than treating jawline definition as an isolated aesthetic goal.
A more angular jawline is not necessarily a better jawline. The aim should be a result that respects the individual’s natural anatomy and proportions.
The importance of realistic expectations
One of the most valuable parts of a consultation is discussing what can realistically be achieved.
Every person has different bone structure, muscle size, fat distribution and skin characteristics. These differences influence both the available options and their potential results.
It is also important to consider how the face changes over time. Natural facial fullness, tissue support and skin elasticity can change with age, and an approach that seems appealing at one stage of life may not be appropriate for another.
A thorough assessment allows these factors to be considered before any decision is made.
My approach is to explain the anatomy, discuss appropriate options and their limitations, and help patients understand what is realistic for them as an individual.
Sometimes, that means discussing treatment. Sometimes, it means explaining why a particular concern cannot be addressed in the way someone initially imagined. And sometimes, it means recommending no treatment at all.
Considering jawline treatment? Start with an assessment.
If your jawline blends into your neck, you have noticed changes in your lower face or you feel your facial contours have become less distinct, the first step is understanding why.
Muscle, fat, skin laxity and the underlying jawbone can all influence the appearance of the jawline. The chin and surrounding facial structures also play an important role.
A personalised consultation allows these factors to be assessed together, rather than assuming the visible concern tells the whole story.
My approach is grounded in anatomical assessment, patient education and realistic expectations. The aim is to help you understand your facial structure and make an informed decision about whether any intervention is appropriate.
To discuss your concerns, you can arrange a consultation at 3 locations across Sydney in Surry Hills, Mosman or Penrith.
Frequently Asked Questions
There is no single best treatment for everyone. Jawline definition can be influenced by muscle size, subcutaneous fat, skin laxity, jowling and underlying bone structure. A personalised assessment helps identify the contributing factors and determine which options, if any, may be appropriate.
A less distinct jaw-to-neck angle can be influenced by fullness beneath the chin, soft-tissue distribution, skin laxity, the position of the chin and the underlying jawbone. Head position can also change the appearance of this area. An assessment is needed to distinguish between these factors.
Depending on the cause of the concern, surgical and non-surgical approaches may be considered upon consultation. However, not every anatomical concern can be addressed effectively without surgery, and some may not be suitable for treatment. The appropriate options depend on your anatomy, goals and individual suitability.
Fat-related fullness and skin laxity can look similar, and both can occur together. An assessment considers the distribution of fullness, skin elasticity, tissue mobility and the underlying facial structure. The distinction matters because addressing one factor does not necessarily address the other.
Repeated clenching or grinding can contribute to enlargement of the masseter muscles in some people. Because these muscles sit at the sides of the jaw, increased muscle bulk can make the lower face appear wider or squarer. However, facial width is also influenced by natural muscle size, bone structure and soft-tissue distribution.
Jowls develop through a combination of age-related changes in skin elasticity, facial fat distribution and the supporting tissues of the lower face. The most appropriate management depends on the degree of tissue laxity, the underlying anatomy and the individual’s goals. Non-surgical approaches have limitations, and a consultation can help clarify which options may be suitable.
Yes. A receded chin can alter the side-profile relationship between the chin, lower jaw and neck, making the jawline appear less distinct. This is why chin projection should be assessed alongside the jawline rather than assuming the concern originates solely from the jaw angle or soft tissues.
Age-related changes can affect boney support, skin elasticity, facial fat distribution, soft-tissue support and the appearance of the lower face. These changes occur at different rates in different people. Genetics, natural facial structure and muscle activity can also influence how the jawline changes over time.
No. Natural variation in bone structure, chin projection, muscle size and soft-tissue distribution means that jawlines differ considerably. An angular contour that suits one person may not be achievable or harmonious for another. Realistic expectations should be based on individual anatomy rather than comparison with photographs online.
No. A wider or fuller lower face may reflect natural bone structure, muscle bulk or soft-tissue distribution. In some people, natural fullness contributes to facial balance and youthful appearance. An assessment can help determine whether there is an identifiable concern that is appropriate to address, or whether maintaining the existing anatomy is the better choice.
A consultation generally involves discussing your concerns and goals, medical history, assessing the face from the front and side, and examining relevant anatomical factors such as muscle activity, chin projection, bone structure, soft-tissue fullness and skin laxity. Your practitioner can then explain the relevant findings, discuss potential suitable options if appropriate, their limitations, risks, pricing, and help you with the next steps. Consultations do not guarantee treatment. Treatment results vary from person-to-person and from treatment-to-treatment.